
Two Years After the Change Healthcare Cyberattack, Healthcare Still Has a Clearinghouse Redundancy Problem
What happened was not just a cybersecurity failure, it was an infrastructure failure.
What happened was not just a cybersecurity failure, it was an infrastructure failure.
The path forward requires much more than whack-a-mole point solution replacement. It requires a more critical look at redesigning the entire workflow architecture


What if health plans could identify member decline before an avoidable hospitalization occurs? Real-time clinical visibility into long-stay SNF members uncovers risk earlier and drives better outcomes.

Most younger professionals entering the workforce have little visibility into interoperability, digital health infrastructure, or healthcare data architecture as career pathways.
The industry has made real progress in recognizing that oral health belongs at the center of whole-person care, but intent alone isn’t enough. To translate this vision into something tangible, the industry must invest in infrastructure that makes integration not only possible but scalable.

The PBM reform efforts are directional, not temporary. Meeting these expectations requires automated systems that can reconstruct claim logic on demand and provide real-time alignment between pricing, rebates and financial outputs.

Healthcare needs systems that work for providers, for health plans, and most importantly, for patients. And that starts with designing not just for technology, but for the people who depend on it, people who need to trust it will work when it matters most.


In an interview, Kyan Health Co-Founder and Chief Commercial Officer Konstantin Struck discussed how Kyan gives mid-market and enterprise employers access to premium workforce mental healthcare, at a price point that is affordable.

Rural healthcare has always run on ingenuity, resilience, and community trust. What has too often been missing is the infrastructure strong enough to match that and sustain it at scale. That is what makes this moment different.

In dental practices, where reimbursement cycles are tighter and administrative inefficiencies are immediately visible, AI is already being evaluated not for novelty, but for operational impact.

As commercialization increasingly reflects direct engagement dynamics, differentiation depends less on the volume of data controlled and more on the speed at which systems incorporate feedback.

For patients, recalls can fail to protect them — not because they came too late, but because they stop at notification and never fully translate into action.

We are taking a look at how health insurers are using AI, defining success, and managing cybersecurity risks. Give us your opinions by completing our brief, anonymous survey.

Shifting healthcare dollars into individual-controlled accounts would mark an inflection point. But even without full policy execution, consumer wallet economics are expanding. The race is now on to build the infrastructure layer between individual spending authority and care delivery.

Personalized and highly-targeted therapeutics are becoming more common, making local or regional production increasingly valuable for faster patient access. This underscores how a hybrid network combining large, centralized plants coupled with flexible regional sites will define the next era of resilient biomanufacturing.
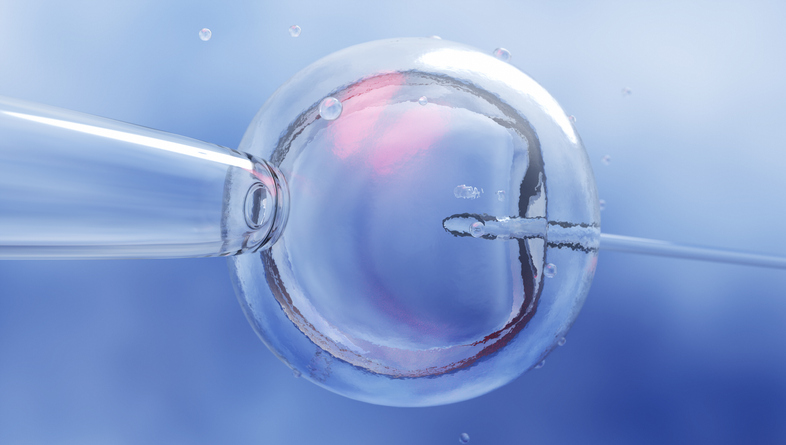
Ideas floated by the Trump Administration and Democrats in Congress aim to expand access to fertility treatment as an essential health benefit. But an influx of patients could collide with an already-brittle system of 430,000 annual cycles, 5,000 embryologists, and long-overdue lab upgrades.

The real story isn’t about denial rates or stakeholders acting as villains. It’s about a healthcare system that forces intelligent, well-intentioned professionals to make critical decisions in information silos.

It’s a meaningful step. But declarations alone won’t fix a system still powered by fax machines, phone calls, and inconsistent rules. Real progress will require a modern digital infrastructure, aligned incentives, and coordinated action across both the public and private sectors.